
 ×

The Short Answer: A NICU feeding protocol is a standardized plan that guides how preterm and sick newborns are fed at each stage of care, including parenteral nutrition, enteral feeds, and full oral feeding. Consistent feeding protocols lower the risk of complications like necrotizing enterocolitis, and support consistent documentation that can help units demonstrate adherence to their feeding policies and prepare for quality or accreditation review.
Feeding a premature infant is one of the more complex daily tasks in the neonatal intensive care unit. Each baby has a different gestational age, birth weight, and clinical status, and small errors carry real consequences. A clear protocol gives NICU nurses, neonatologists, dietitians, and occupational therapists a shared roadmap. It also helps care teams record every feed, which matters for both patient safety and audit readiness.
A NICU feeding protocol is a written, standardized approach to feeding preterm infants and other babies in intensive care. Instead of leaving each feeding decision to individual judgment, the protocol sets criteria for when and how to start, advance, and adjust feeds.
A typical protocol covers:
The goal is consistency. When every neonatal professional follows the same feeding practices, care becomes more predictable and easier to document.
Many very preterm or medically complex infants progress through several feeding phases during their NICU stay. A protocol maps each step, where components/phases may overlap as feeding progresses.
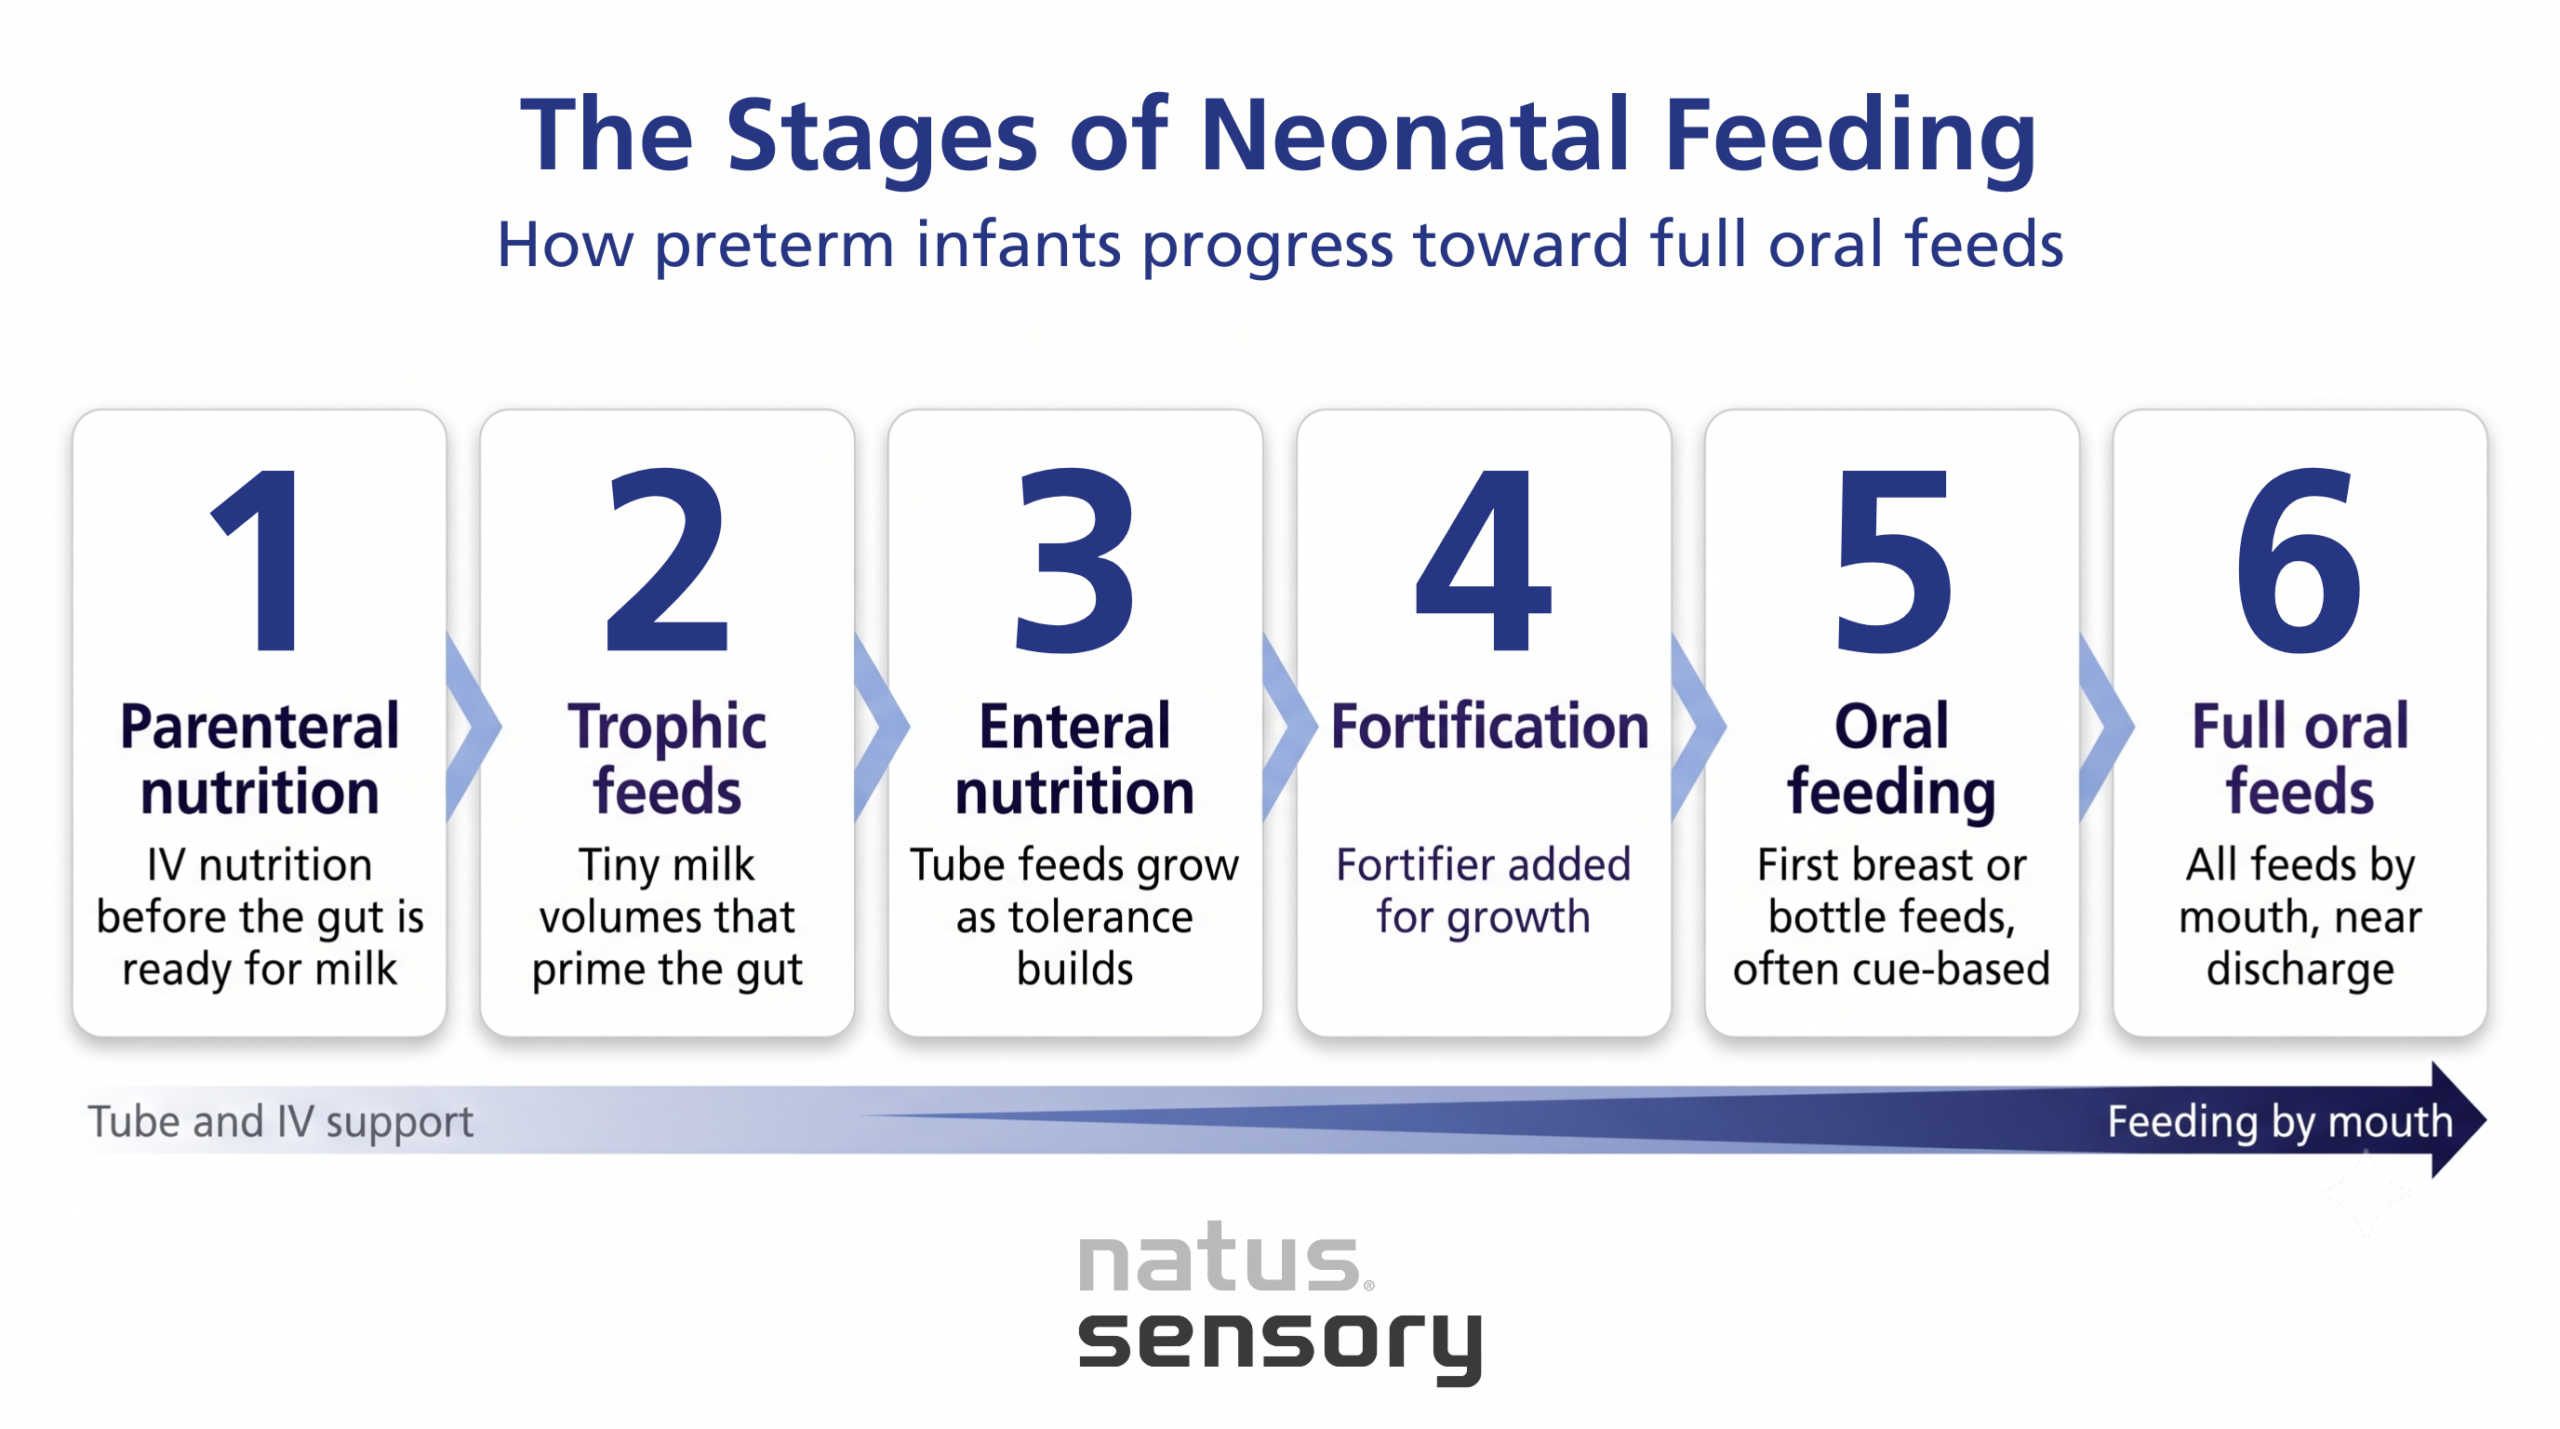
A feeding protocol works only when the whole care team follows it. Several roles share the job:
This shared structure also supports developmental care, since a steady routine lowers stress for the infant and gives parents a clearer role at the bedside. Clear hand-offs between roles keep the protocol consistent across every shift, even as a baby’s clinical status changes.
The strongest argument for a NICU feeding protocol is patient safety. Necrotizing enterocolitis (NEC) is a serious intestinal medical condition that mostly affects premature infants, and feeding practices influence the risk.
A systematic review in Archives of Disease in Childhood found substantially lower NEC incidence following implementation of standardized feeding regimens.
Standardized protocols help by:
Traditional volume-driven approaches often used predetermined feeding volumes and schedules. Many units now use cue-based feeding, which uses the infant’s readiness, hunger, satiation and physiologic stability cues to guide oral feeding.
Reading infant behavior matters because a premature baby has to coordinate sucking, swallowing, and breathing before oral feeding is safe. Occupational therapists and NICU nurses watch for cues that the infant is ready.
A 2023 study in Scientific Reports found that a cue-based feeding protocol was tied to a shorter time to full oral feeds and a drop in median length of stay, from 55 to 48 days, in very low birth weight infants. A separate study in Frontiers in Pediatrics found that preterm infants on cue-based feeding reached full oral feeding faster and at an earlier gestational age than those on volume-driven feeds.
This approach supports developmentally responsive care by allowing feeding progression to reflect the infant’s readiness and physiologic cues.
Human milk is the first choice for premature infants. Both mother’s own breast milk and pasteurized donor milk are linked to lower NEC risk compared with preterm formula.
Because human milk alone may not meet the needs of very low birth weight infants, many protocols add a fortifier once enteral feeds reach a set volume. Clinicians can choose a human milk-based fortifier or a cow milk-based fortifier, and research on the trade-offs continues A review from the European Milk Bank Association notes that fortification is recommended for very low birth weight and other preterm infants whose nutritional requirements exceed those provided by unfortified human milk.
Tracking which milk, which fortifier, and which expiration date applies to each baby is where feeding gets complicated fast.
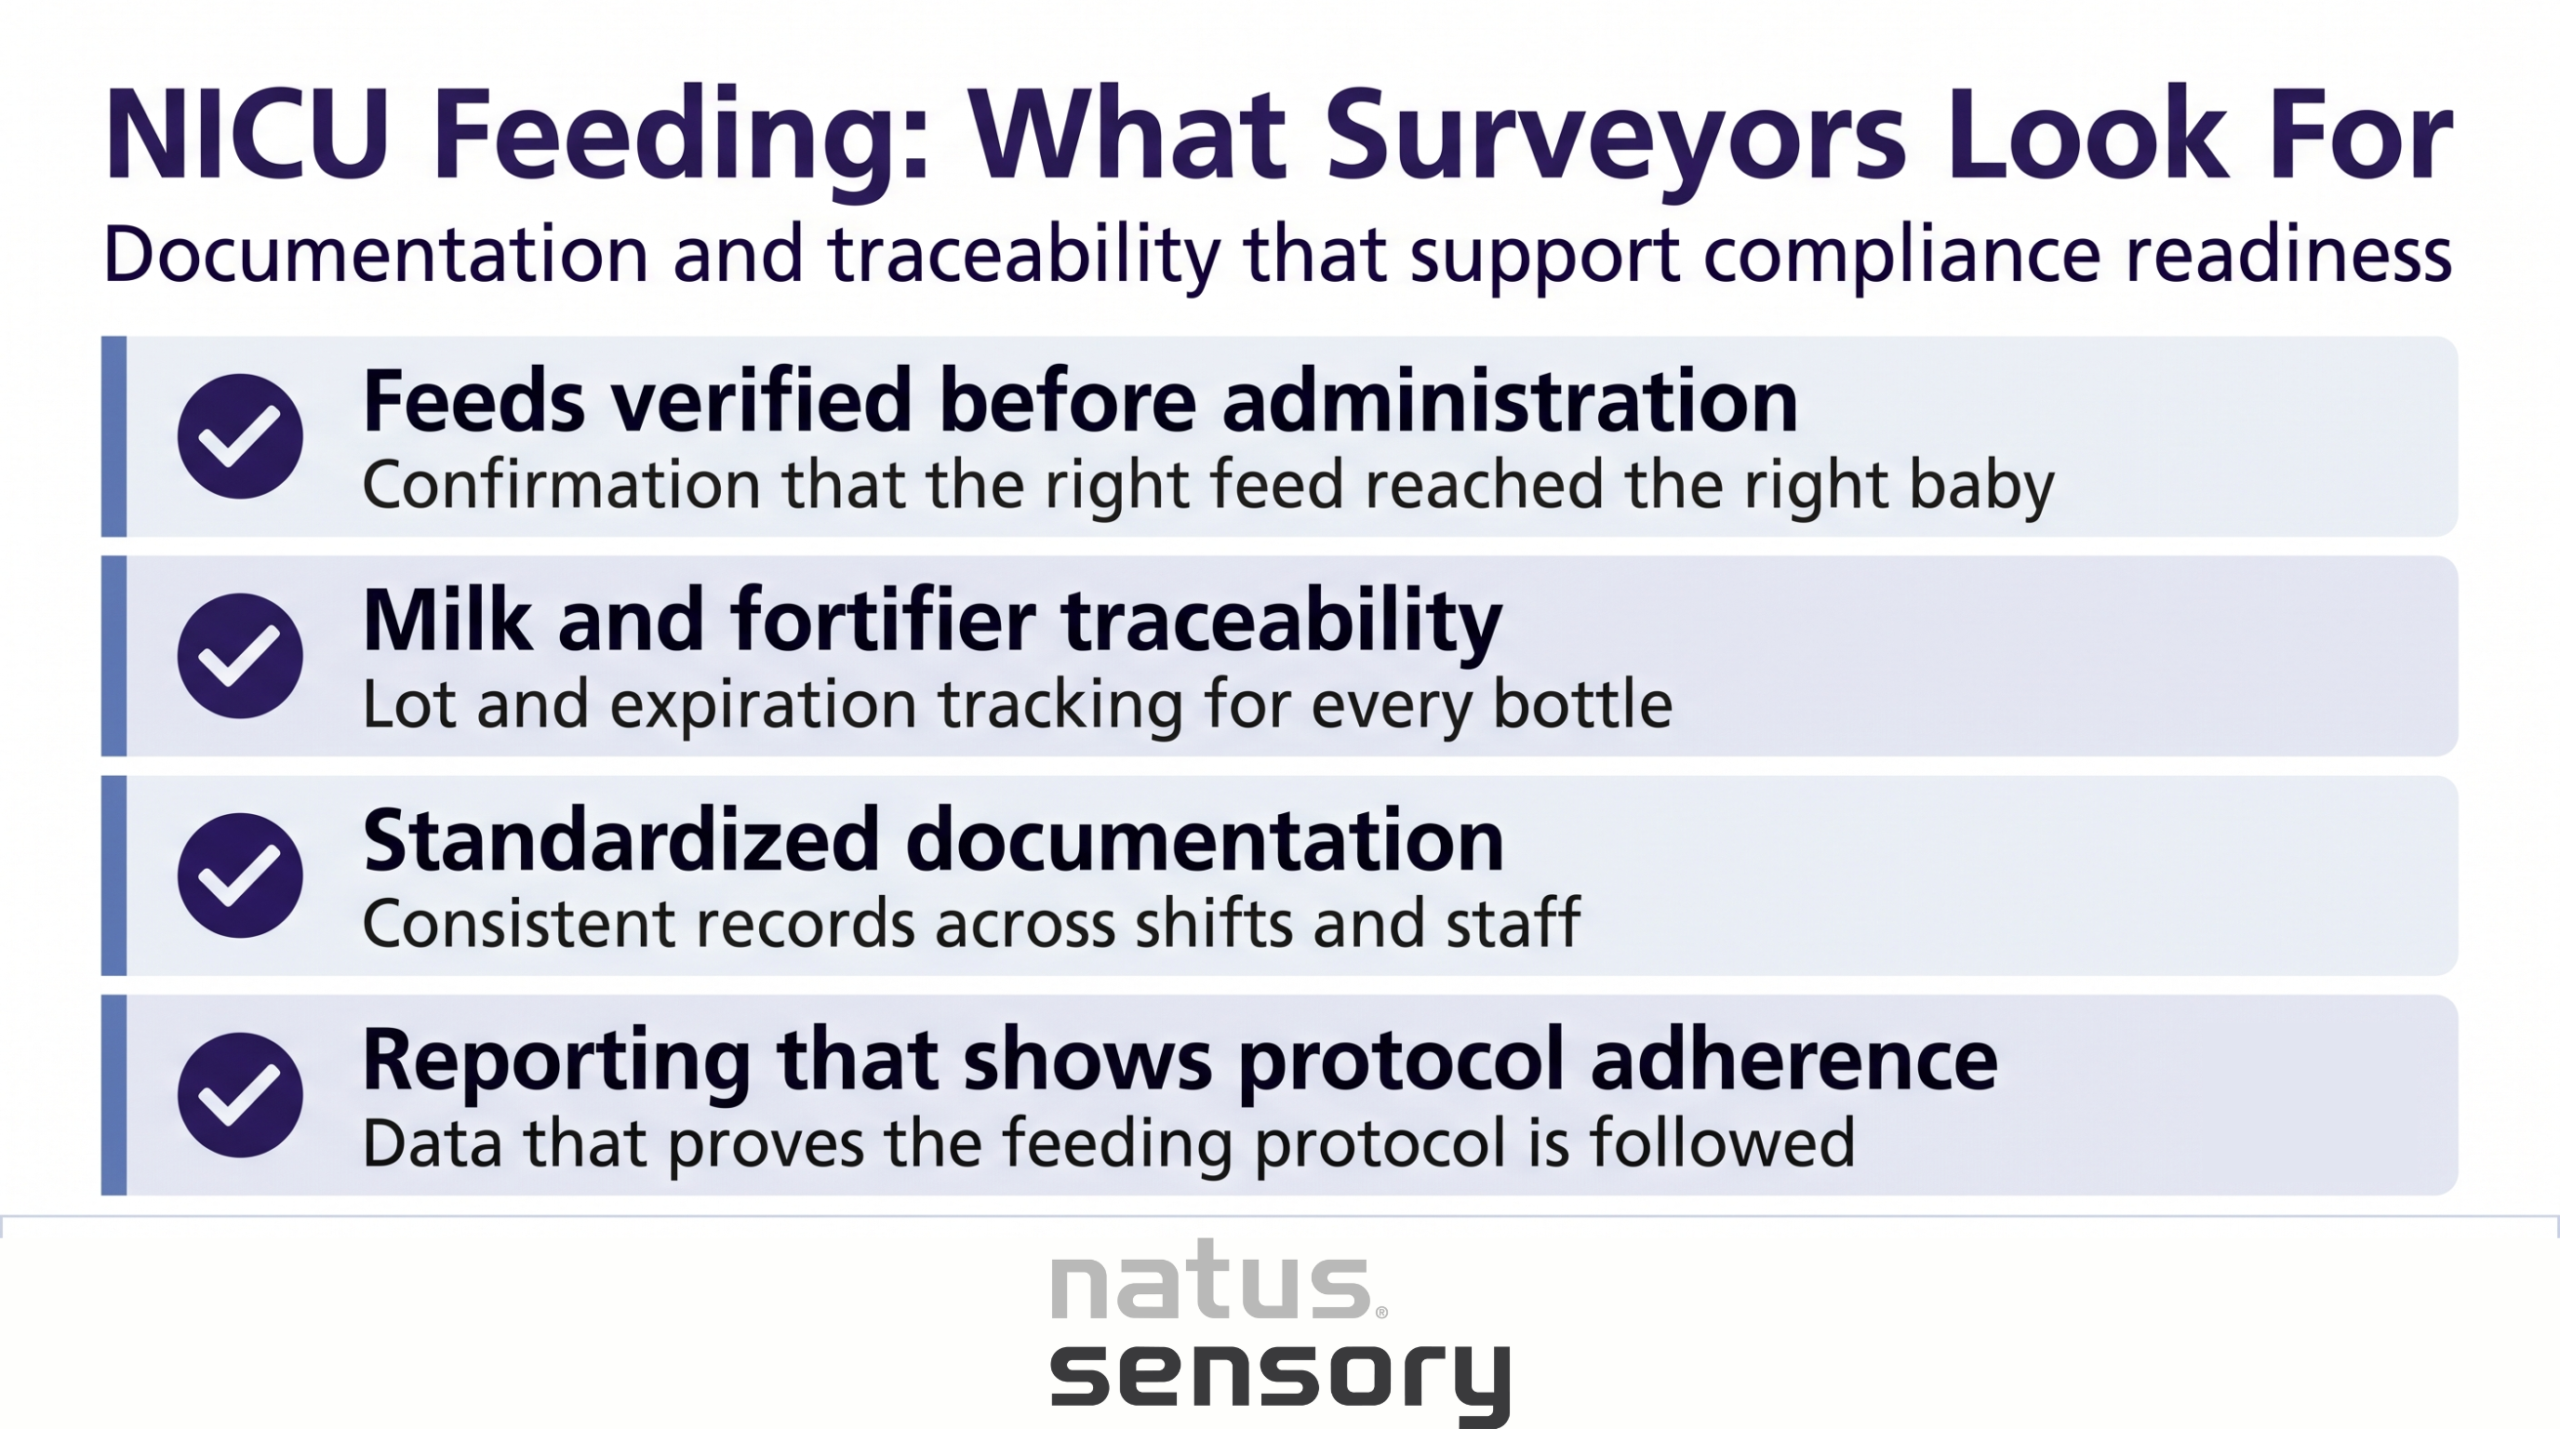
Every feed in the NICU is a chance for an error: the wrong milk, an expired bottle, or a missed fortification step. Giving one mother’s breast milk to the wrong infant is a recognized safety event that carries increased risk for vulnerable babies.
This is where documentation and traceability earn their place. An open-access review in Frontiers in Nutrition describes how barcode scanning and centralized milk handling have become recognized best practices for catching misidentification, expired milk, and fortification errors before a feed reaches the baby.
Strong feeding records also support compliance. Surveyors and accreditation bodies look for:
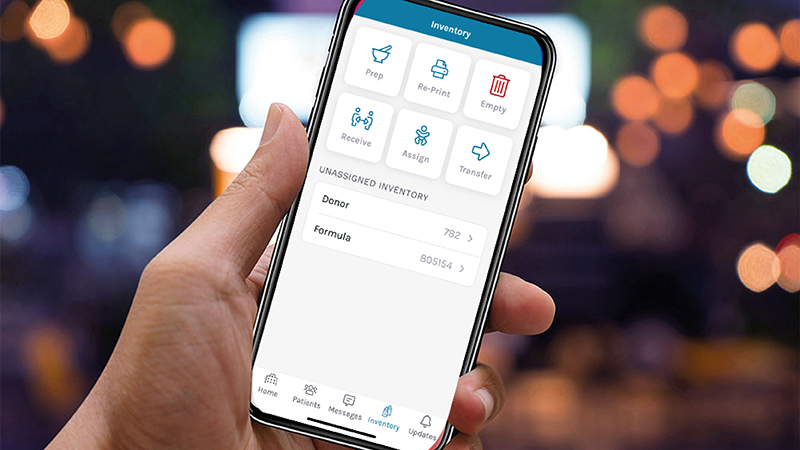
Manual tracking with handwritten labels and two-nurse checks is hard to sustain across a busy unit. Connected feeding management tools help by handling the repetitive parts of the protocol.
These systems can:
The result is a feeding workflow that is easier to follow and easier to prove during an audit.
Building safer feeding workflows with confidence
A NICU feeding protocol turns a high-stakes, detail-heavy process into something consistent and traceable. Standardized feeding lowers the risk of NEC, cue-based feeding supports a smoother path to full oral feeds, and human milk with appropriate fortification gives preterm infants a strong nutritional start. Behind each of these steps sits the same need: accurate records that support traceability, quality review and demonstration of adherence to unit protocols.
Natus Sensory supports safer neonatal feeding through Keriton, a feeding management platform built for the NICU. Keriton uses multilayered barcode validation to confirm the right feed for the right baby, automates fortification calculations, and keeps milk and formula traceable at each step of preparation and administration. To see how Keriton can support your unit’s feeding workflows and compliance readiness, explore our newborn care solutions or contact our team.
Sources:
054399 RevA